
 KES

Articles
- Page Path
- HOME > Endocrinol Metab > Volume 33(2); 2018 > Article
-
Review ArticleManagement of Low-Risk Papillary Thyroid Cancer
-
Nicole M. Iñiguez-Ariza1,2
 , Juan P. Brito2,3
-
Endocrinology and Metabolism 2018;33(2):185-194.
DOI: https://doi.org/10.3803/EnM.2018.33.2.185
Published online: June 21, 2018
1Department of Endocrinology and Metabolism, Instituto Nacional de Ciencias Médicas y Nutrición Salvador Zubirán, Mexico City, Mexico.
2Division of Endocrinology, Diabetes, Metabolism, and Nutrition, Mayo Clinic, Rochester, MN, USA.
3Knowledge and Evaluation Research Unit, Mayo Clinic, Rochester, MN, USA.
- Corresponding author: Juan P. Brito. Division of Endocrinology, Diabetes, Metabolism, and Nutrition, and Knowledge and Evaluation Research Unit, Mayo Clinic, 200 First St. SW, Rochester, MN 55905, USA. Tel: +1-507-284-2463, Fax: +1-507-284-5745, brito.juan@mayo.edu
Copyright © 2018 Korean Endocrine Society
This is an Open Access article distributed under the terms of the Creative Commons Attribution Non-Commercial License (http://creativecommons.org/licenses/by-nc/4.0/) which permits unrestricted non-commercial use, distribution, and reproduction in any medium, provided the original work is properly cited.

ABSTRACT
- The incidence of thyroid cancer has increased, mainly due to the incidental finding of low-risk papillary thyroid cancers (PTC). These malignancies grow slowly, and are unlikely to cause morbidity and mortality. New understanding about the prognosis of tumor features has led to reclassification of many tumors within the low-risk thyroid category, and to the development of a new one “very low-risk tumors.” Alternative less aggressive approaches to therapy are now available including active surveillance and minimally invasive interventions. In this narrative review, we have summarized the available evidence for the management of low-risk PTC.
- Over the past 20 to 30 years there has been an increase in the incidence of thyroid cancers in industrialized countries, with stable or little change in mortality [1234]. The majority of the new thyroid cancer cases are small papillary thyroid cancers (PTCs). These small low-risk lesions are often found incidentally, and in patients without any symptoms [56]. This change in the epidemiology of thyroid cancer has implications on the management of this disease. The traditional paradigm of treating all patients with thyroid cancer with surgery, radioactive iodine (RAI), and suppressive thyroid hormone therapy is no longer suitable. Rather, patients with thyroid cancer should receive treatment according to their overall prognosis, recurrent and mortality risks, the treatment's benefits and harms, and the patient's context and values. In this review, we describe new elements of the individualized approach for the management of low-risk thyroid cancers.
INTRODUCTION
- Low-risk thyroid cancers are those malignancies unlikely to recur, and to cause morbidity and mortality. Although, this definition was used mostly to describe intrathyroidal micropapillary cancers, recent changes in several scoring systems have expanded this definition to include tumors with other pathological features within the low-risk category (Tables 1, 2) [789].
- Some of the changes reflect a better understanding of patient and tumor features not associated with increases in cancer specific mortality. The American Joint Committee on Cancer (AJCC)/tumor size and invasion, regional lymph nodes status and distant metastatic spread (TNM) cancer staging system (a system that provides stages associated with risk of cancer mortality) [9] changed the age cut-off for the diagnosis of thyroid cancer, increasing it from 45 to 55 years of age, with consequent down staging of 12% of patients into a low-risk category (Stage I), without significantly altering the mortality associated with the various stages. Another change in the staging system is that minor extrathyroidal extension (ETE) detected on histological examination only was deemed to be a low-risk feature. Although previous literature considered both gross and minimal ETE as risk factors for recurrence [10]; microscopic ETE remained a topic of controversy. The change to the TNM system is consistent with newer evidence showing that minimal ETE in PTC does not result in increased rates of either cause-specific mortality or postoperative tumor recurrence [111213]. As a consequence of these changes, the 8th edition of the AJCC/TNM for differentiated thyroid cancer results in more patients being adequately classified as low-risk (Stage I or II). A necessary consequence of the decanting of low-risk patients from the high-risk category however, is that epidemiologically the average prognosis for the patients remaining in the high-risk category is poorer.
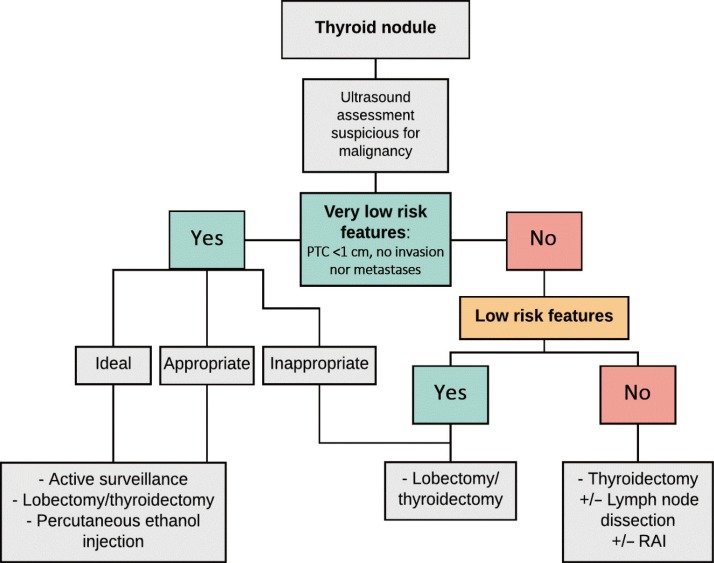
- To further refine the category of low-risk, the American Thyroid Association (ATA) guideline created a subcategory of “very low-risk tumors.” These tumors are subcentimeter PTC without clinically evident metastases or local invasion and no cytologic evidence of aggressive disease. This change is important as it recognizes the low-risk of mortality in patients with tumors with these features and may lead patients and their clinicians to consider less aggressive options such as active surveillance to manage these tumors (Table 2, Fig. 1) [7].
- The ATA, in an additional effort to highlight the low-risk of mortality with certain tumors, has also recognized that “Non-Invasive Follicular Thyroid neoplasm with Papillary-like nuclear features (NIFTP)” are low-risk. These tumors, previously called non-invasive encapsulated follicular variant of papillary thyroid cancer, have a <1% risk of recurrence in 15 years [14]. By changing the nomenclature and removing the cancer label, experts hope to reduce unnecessary post-thyroidectomy treatments (e.g., RAI), to reduce the intensity of follow-up, and improve patients' emotional well-being [1516171819].
- Beyond better differentiating high-risk and low-risk tumors, the updated guidelines modified the stratification system used for risk of recurrence [7]. Intrathyroidal PTC with ≤5 small volume lymph node (<0.2 cm) metastases, previously classified as intermediate [20] is now classified as low-risk. Other features that indicate a low-risk of recurrence include: intrathyroidal encapsulated follicular variant PTC, intrathyroidal well differentiated follicular thyroid cancer with capsular invasion and no or minimal (<4 foci) vascular invasion and intrathyroidal papillary microcarcinoma, unifocal or multifocal, including BRAFV600E mutated (if known) (Table 1). Despite emerging evidence to the contrary [111213], the ATA chose to keep microscopic ETE as an indicator of intermediate risk of recurrence.
THE DEFINITION OF LOW-RISK THYROID CANCER HAS EXPANDED
- Active surveillance for subcentimeter papillary thyroid cancer
- In the 1990s the natural history of small PTC was not clear, but it was thought that most would not grow over time or would grow very slowly. Based on this hypothesis Miyauchi et al. [21], proposed a clinical trial of observation without immediate surgery for subcentimeter PTCs at Kuma Hospital, later called “active surveillance.” Patients with subcentimeter low-risk PTC were offered active surveillance or immediate surgery as alternatives. For those who chose “active surveillance,” ultrasound was performed every 6 months after diagnosis and once a year thereafter. Surgery was recommended when tumors grew by ≥3 mm or when novel lymph node metastasis developed [21].
- By 2014, they had enrolled 1,235 patients, and showed that only 8% of subcentimeter low-risk PTC had a size enlargement of >3 mm and only 3.8% were found to have novel regional nodal metastases after a 10-year observation period and none of the 1,235 patients showed distant metastasis or died from subcentimeter low-risk PTC [2223]. They also noted that young patients (<40 years) were more likely to experience thyroid tumor enlargement and novel lymph node appearance compared with middle-age (40 to 59 years) or older patients (>60 years). Similarly, in 2010, the Tokyo Cancer Institute Hospital group reported [24] their findings on active surveillance of 300 lesions in 230 patients for a mean of 5 years (range, 1 to 17). They showed that only 7% had size enlargement during “active-surveillance” protocol, 90% had remained unchanged and 3% decreased in size. No patient developed extrathyroidal invasion or distant metastasis. Both groups data showed that rescue surgery after progression was detected was successful and no life-threatening recurrence was detected thereafter [2224]. The results of these landmarks studies have demonstrated that active surveillance is a safe and adequate treatment for properly selected patients with subcentimeter low-risk PTC [212526].
- To assess if a patient with subcentimeter low-risk PTC is suitable for an “active surveillance” approach, a variety of factors should be taken into consideration. The Memorial Sloan Kettering Cancer Center (MSKCC) in collaboration with the Kuma Hospital group developed a clinical framework to assess suitability for an “active surveillance” approach. The rationale for the development of this risk-stratified clinical decision-making framework is that though the 2015 ATA guidelines endorse “active surveillance” as an alternative to immediate biopsy and surgery in subcentimeter thyroid nodules with highly suspicious ultrasonographic characteristics, as well as in cyto-confirmed very low-risk PTC; the guidelines do not specify how to properly select patients for an “active surveillance” approach. In this framework, patients are divided in distinct categories: ideal, appropriate and inappropriate candidates for “active surveillance” based on a variety of factors (inherent to the tumor, patient characteristics and medical team characteristics) (Table 3) [27]. An “ideal” candidate, would be an older patient (>60 years old), with a subcentimeter low-risk PTC (probable or proven), with regular margins, confined to the thyroid parenchyma and not adjacent to the thyroid capsule. An “appropriate” candidate, would be younger, with tumor multifocality, with potentially aggressive molecular phenotype, adjacent to thyroid capsule but not in risky-zones, or have other imaging findings that can make follow-up more problematic (e.g., thyroiditis, other benign-appearing nodules, nonspecific lymph nodes). An “inappropriate” candidate, has tumors at risky-subcapsular locations (e.g., adjacent to the trachea or recurrent laryngeal nerve), has evidence of loco-regional or distant spread, or has evidence of disease progression on serial examinations.
- Patients in the “ideal” category demonstrate a <2% rate of disease progression, and should be offered active surveillance. On the other hand, patients in the “appropriate” category might demonstrate a 10% rate of disease progression, and active surveillance may be offered by an experienced management team, as delayed surgery will still be effective, with good clinical outcomes. Finally, patients in the “inappropriate” category should not be offered active surveillance given the possibility that minor disease progression could lead to significant morbidity, and because a high rate of disease progression is expected.
- Despite the potential benefits of active surveillance for some patients with very low-risk thyroid cancer, this management option has not been widely adopted. One potential barrier is that clinicians may have difficulty communicating the comparative benefits and downsides of the treatment options, and understanding patients' treatment preferences. Recently, and to support decision making for patients with subcentimeter low-risk PTC, researchers from MSKCC and Mayo Clinic in the United States developed a decision aid for use in clinical encounters called Thyroid Cancer Choice (TCC). This tool includes (1) an estimate of the frequency of thyroid cancer in the population; (2) the management options, active surveillance and thyroid surgery; (3) the risk of death, metastasis, tumor growth and adverse effects with each option; (4) the planned type and frequency of follow-up; (5) the out-of-pocket costs with each choice; and (6) the interaction of pregnancy and each management option. A Korean adaption of this tool underwent pilot testing at Seoul National University Hospital and Seoul National University Bundang Hospital, and found that among the 220 patients with small PTC, patients using TCC were more likely to choose active surveillance than the patients seen in the usual care clinic (relative risk, 1.16; 95% confidence interval, 1.04 to 1.29). Although this result suggests that this tool increases acceptance of active surveillance, additional and more rigorous studies are needed to confirm this finding.
- To further assess active surveillance of subcentimeter low-risk PTC in different populations, Seoul, Korea has two ongoing recruiting studies (NCT02952612 and NCT02938702; both require fine needle aspiration [FNA] diagnosis to be performed as a criteria of inclusion). And there is another study (NCT03327636) expected to start recruiting on June 2018 in Hong Kong, China, it is a randomized study comparing high intensity focus ultrasound (HIFU) versus active surveillance for the management approach of subcentimeter PTC confirmed on FNA (Bethesda V or VI).
- Active surveillance for larger papillary thyroid cancers
- As described above, the initial studies of active surveillance were conducted in patients with subcentimeter tumors. As the comfort with active surveillance grows, clinicians are exploring the appropriateness of active surveillance in patients with larger tumors, specifically those ≤1.5 cm.
- Building on the experience from the two cohorts in Japan, Tuttle et al. [28] developed an active surveillance cohort at MSKCC. The cohort consisted of 291 patients with low-risk PTC (≤1.5 cm) followed by a median of 25 months (range, 6 to 166). Consistent with previous reports, growth in tumor diameter ≥3 mm was observed in 11 of 291 (3.8%), with a cumulative incidence of 2.5% (2 years) and 12.1% (5 years). No regional or distant metastases developed during “active surveillance.” They also noticed that the tumor growth follows an exponential pattern with a median doubling time of 2.2 years (range, 0.5 to 4.8) indicating the change in tumor size could be modeled and predicted (Table 4). Other studies assessing the possibility of active surveillance for larger low-risk PTC tumors are currently active at different locations. There is a study (NCT03271892) recruiting patients 18 years of age or older with newly diagnosed previously untreated PTC (FNA biopsy positive for PTC or suspicious for PTC) and a tumor size <2 cm in maximal diameter on thyroid ultrasound, with no evidence of lymph node and/or distant metastatic disease. The study, based in Toronto, started in May 2016 and the estimated completion date of the study is May 2026. Another study (NCT02609685), being conducted in Los Angeles, is recruiting adult patients with pathologically confirmed Bethesda V or VI thyroid nodules with PTC and ≤1.5 cm, the study started in December 2015 and the estimated primary completion date is December 2030.
- Lobectomy as a treatment option for low-risk cancers
- As the role of active surveillance has expanded, so has the role of lobectomy as a treatment option for low-risk tumors. Previously, lobectomy was only indicated for unifocal tumors <1 cm in size without preoperative evidence of extrathyroid extension or lymph node metastases (cN0). More recent evidence however, suggests that lobectomy can be safely performed in patients with larger tumors [2930]. Lobectomy is most commonly performed using a transcervical approach (collar incision) under general anesthesia. However, a variety of minimally invasive techniques have been developed which are appropriate for low-risk tumors. These approaches often leave no obvious scar, a patient important outcome, and include techniques such as: endoscopic thyroidectomy using transaxillary approach, anterior chest, breast, “facelift” or even transoral endoscopic thyroidectomy via a vestibular approach (TOETVA). TOETVA is a novel, scar-free procedure that has no visible incisions [31].
- For low-risk PTC, the decision to perform a total thyroidectomy or a lobectomy must be based on accurate and complete preoperative assessment as to the extent of the disease and after properly assessing patient's preferences. Thyroid surgery should be performed by high-volume surgeons (>25 thyroid surgeries yearly) at high-volume centers to avoid higher rates of surgical complications [323334]. Furthermore, thyroidectomy without prophylactic central neck dissection is appropriate for low-risk thyroid cancer.
- It is important to properly assess the benefits and harms of each particular therapy and to set expectations clear upfront to patients, so they engage fully in a conversation around what is the best therapy for them. The advantages of near total or total thyroidectomy is the ease of follow-up and the capability of administering RAI though, RAI has very limited role in the treatment of low-risk PTC; patients treated without RAI have similar survival rates. The disadvantages of total or near total thyroidectomy are that it is associated with higher surgical risks (e.g., transient or permanent post-surgical hypoparathyroidism, recurrent laryngeal nerve injury unilateral or bilateral, hematoma formation, infection and even chyle leak with unexperienced surgeons when thyroidectomy is combined with prophylactic node dissection) and the necessity of thyroid hormone replacement in all. The lobectomy has the advantages of lower surgical risks (e.g., unilateral recurrent laryngeal nerve injury, transient hypoparathyroidism, hematoma, infection) and only around 50% of patients will require thyroid hormone replacement after surgery [35]. The disadvantages are that biochemical follow-up is not as straightforward; therefore, the follow-up should rely more on structural serial-imaging assessment and some patients might require a second surgery to remove the contralateral lobe in the future.
- Systemic therapy with RAI and thyroid stimulating hormone suppression
- Radioactive remnant ablation (RRA) is the process by which the administration of RAI is given to treat any possible remnant of “normal” thyroid tissue, while RAI for therapeutic adjuvant purposes is used when we know there is disease left, like due to incomplete tumor resection with “gross residual disease” [36]. The doses vary for RRA and therapeutic RAI, with 30 mCi now considered appropriate to ablate the remnants in selected patients and higher doses administered in the setting of adjuvant therapeutic doses [7].
- The goal of RAI is to reduce risk of recurrence and mortality, and to facilitate follow-up. When deciding if a patient is candidate for RAI, using validated scoring systems to determine the risks of recurrence and mortality, as well as to having a thorough conversation with the endocrine surgeon as to determine if there was any disease left is imperative [93738]. Patients with low-risk PTC have an excellent survival, with rates at 30 postoperative years of only 1% cause-specific-mortality and <15% tumor recurrence at any site [39]. Patients with high-risk for recurrence or mortality are good candidates for RAI because of the absolute benefit of this therapy is higher (higher risk and higher benefit from the intervention). For patients with low and intermediate risk, the decision to treat with RAI should be an individualized one. Most recent systematic reviews and meta-analysis suggest that overwhelming evidence shows that RAI has no role in improving survival or recurrent rates of low-risk PTC [4041]. This body of evidence suggests that the only role for RAI in low-risk patients is to facilitate follow-up. Though, low-risk PTC patients treated with total thyroidectomy and without RAI can be safely and easily followed by ultrasound assessment and thyroglobulin (TG) trend overtime. Furthermore, they tend to have low TG levels and the levels tend to spontaneously drop over time [42].
- For low-risk PTC, thyroid stimulating hormone (TSH) suppression is generally not recommended. The goal of L-thyroxine treatment among low-risk patients is to restore euthyroidism, and to avoid iatrogenic hyperthyroidism, with a TSH goal of 0.5 to 2.0 mU/L [7].
- Alternative minimally invasive therapies
- Percutaneous ethanol injection (PEI) is an option for some patients who are uncomfortable with both surgery and active surveillance. Hay et al. [43] showed their results after ablating 17 biopsy-proven tumor foci in 15 patients with subcentimeter low-risk PTC (two-multicentric). Tumor diameters ranged from 4 to 10 mm (median, 7), patients were followed for 4 to 91 months (mean, 36). All tumor foci treated with PEI decreased in size (diameter and volume), no patient developed neck nodal metastases, neck tenderness lasted hours only and no patient experienced hoarseness. The median tumor volume reduction in the 17 tumor foci at last follow-up was 79% (range, 48% to 100%), at latest assessment, 11 tumors (65%) were still identifiable, median volume decrease 74%. Six foci in five patients (35%) were no longer identifiable after being followed on average for 11 months (range, 3 to 19). A study (NCT01974284) is being conducted at Yale (anticipated completion 2018) to further evaluate the effectiveness of PEI for low-risk PTC.
- Percutaneous, image-guided, in situ tumor ablation with thermal energy source radiofrequency ablation (RFA) has been an effective minimally invasive approach for the treatment of patients with a variety of primary and secondary malignancies, such as liver tumors [44]. It has also been used for the treatment of benign thyroid nodules, proving to be safe and effective in selected patients with symptomatic thyroid nodules [454647]. The term radiofrequency refers to an alternating electric current oscillating between 200 and 1,200 kHz. Heat results in immediate damage to tumor tissue, significant only in regions very close to the electrode (a few millimeters) [48].
- RFA has been used in the setting of loco-regional recurrences in thyroid cancer [49] and more recently has been administered for the treatment of thyroid cancer primary tumor [5051]. In a study by Zhang et al. [52], ultrasound-guided RFA of subcentimeter low-risk PTC proved to be effective and safe. No suspicious metastatic lymph nodes were detected on follow-up. And no major complications were encountered; one patient had moderate pain and four had transient hoarseness.
- Another minimally invasive thermal ablation technique is the ultrasound-guided percutaneous laser ablation (PLA) that can be a therapeutic option in patients with low-risk PTC and high surgical risk, who do not wish an “active surveillance” approach [53]. The energy delivered by the laser results in tissue destruction and carbonization, leading to lack of viability of subcentimeter low-risk PTC treated with this technique [54]. In a recent publication by Zhou et al. [55], PLA treatment of unifocal T1N0M0 subcentimeter low-risk PTC in 30 patients was evaluated retrospectively, 29 patients were treated successfully under local anesthesia in a single session. At last follow-up, 10 ablation zones (33.3%) had disappeared, and 20 ablation zones (66.67%) remained as scar-like lesions. No regrowth of treated tumors, local recurrence or distant metastases were detected. The procedure was apparently well tolerated without serious complications.
TREATMENT MODALITIES FOR PATIENTS WITH LOW-RISK THYROID CANCER
Percutaneous ethanol injection for primary tumor
Radiofrequency ablation
Ultrasound-guided percutaneous laser ablation
- The definition of low-risk PTC has expanded. The previous notion of “one size fits all” (all surgery, all RAI) is no longer acceptable. Management should be individualized, and after proper assessment of cytologic features, tumor location, evidence or absence of metastatic spread, and after considering patient's values and preferences in terms of what is the best treatment approach for a particular patient in their own context. Newer less aggressive approaches and alternatives exist for the treatment of low-risk PTC, such as active surveillance and minimally invasive therapies in properly selected patients.
CONCLUSIONS
-
CONFLICTS OF INTEREST: No potential conflict of interest relevant to this article was reported.
Article information
- 1. Davies L, Welch HG. Current thyroid cancer trends in the United States. JAMA Otolaryngol Head Neck Surg 2014;140:317–322. ArticlePubMed
- 2. Davies L, Morris LG, Haymart M, Chen AY, Goldenberg D, Morris J, et al. American Association of Clinical Endocrinologists and American College of Endocrinology disease state clinical review: the increasing incidence of thyroid cancer. Endocr Pract 2015;21:686–696. ArticlePubMedPMC
- 3. Vaccarella S, Dal Maso L, Laversanne M, Bray F, Plummer M, Franceschi S. The impact of diagnostic changes on the rise in thyroid cancer incidence: a population-based study in selected high-resource countries. Thyroid 2015;25:1127–1136. ArticlePubMed
- 4. Vaccarella S, Franceschi S, Bray F, Wild CP, Plummer M, Dal Maso L. Worldwide thyroid-cancer epidemic? The increasing impact of overdiagnosis. N Engl J Med 2016;375:614–617. ArticlePubMed
- 5. Guth S, Theune U, Aberle J, Galach A, Bamberger CM. Very high prevalence of thyroid nodules detected by high frequency (13 MHz) ultrasound examination. Eur J Clin Invest 2009;39:699–706. ArticlePubMed
- 6. Dal Maso L, Panato C, Franceschi S, Serraino D, Buzzoni C, Busco S, et al. The impact of overdiagnosis on thyroid cancer epidemic in Italy, 1998-2012. Eur J Cancer 2018;94:6–15. PubMed
- 7. Haugen BR, Alexander EK, Bible KC, Doherty GM, Mandel SJ, Nikiforov YE, et al. 2015 American Thyroid Association management guidelines for adult patients with thyroid nodules and differentiated thyroid cancer: the American Thyroid Association guidelines task force on thyroid nodules and differentiated thyroid cancer. Thyroid 2016;26:1–133. PubMedPMC
- 8. Tarasova VD, Tuttle RM. Current management of low risk differentiated thyroid cancer and papillary microcarcinoma. Clin Oncol (R Coll Radiol) 2017;29:290–297. ArticlePubMed
- 9. Tuttle RM, Haugen B, Perrier ND. Updated American Joint Committee on cancer/tumor-node-metastasis staging system for differentiated and anaplastic thyroid cancer (eighth edition): what changed and why? Thyroid 2017;27:751–756. ArticlePubMedPMC
- 10. Arora N, Turbendian HK, Scognamiglio T, Wagner PL, Goldsmith SJ, Zarnegar R, et al. Extrathyroidal extension is not all equal: implications of macroscopic versus microscopic extent in papillary thyroid carcinoma. Surgery 2008;144:942–947. ArticlePubMed
- 11. Hay ID, Johnson TR, Thompson GB, Sebo TJ, Reinalda MS. Minimal extrathyroid extension in papillary thyroid carcinoma does not result in increased rates of either cause-specific mortality or postoperative tumor recurrence. Surgery 2016;159:11–19. ArticlePubMed
- 12. Jin BJ, Kim MK, Ji YB, Song CM, Park JH, Tae K. Characteristics and significance of minimal and maximal extrathyroidal extension in papillary thyroid carcinoma. Oral Oncol 2015;51:759–763. ArticlePubMed
- 13. Nixon IJ, Ganly I, Patel S, Palmer FL, Whitcher MM, Tuttle RM, et al. The impact of microscopic extrathyroid extension on outcome in patients with clinical T1 and T2 well-differentiated thyroid cancer. Surgery 2011;150:1242–1249. ArticlePubMedPMC
- 14. Nikiforov YE, Seethala RR, Tallini G, Baloch ZW, Basolo F, Thompson LD, et al. Nomenclature revision for encapsulated follicular variant of papillary thyroid carcinoma: a paradigm shift to reduce overtreatment of indolent tumors. JAMA Oncol 2016;2:1023–1029. ArticlePubMedPMC
- 15. Hodak S, Tuttle RM, Maytal G, Nikiforov YE, Randolph G. Changing the cancer diagnosis: the case of follicular variant of papillary thyroid cancer-primum non nocere and NIFTP. Thyroid 2016;26:869–871. ArticlePubMedPDF
- 16. Thompson LD. Ninety-four cases of encapsulated follicular variant of papillary thyroid carcinoma: a name change to noninvasive follicular thyroid neoplasm with papillary-like nuclear features would help prevent overtreatment. Mod Pathol 2016;29:698–707. ArticlePubMedPDF
- 17. Xu B, Tallini G, Ghossein RA. Noninvasive follicular thyroid neoplasm with papillary-like nuclear features: historical context, diagnosis, and future challenges. Endocr Pathol 2017;28:128–138. ArticlePubMedPDF
- 18. Xu B, Tallini G, Scognamiglio T, Roman BR, Tuttle RM, Ghossein RA. Outcome of large noninvasive follicular thyroid neoplasm with papillary-like nuclear features. Thyroid 2017;27:512–517. ArticlePubMedPMC
- 19. Lloyd RV, Asa SL, LiVolsi VA, Sadow PM, Tischler AS, Ghossein RA, et al. The evolving diagnosis of noninvasive follicular thyroid neoplasm with papillary-like nuclear features (NIFTP). Hum Pathol 2018;74:1–4. ArticlePubMed
- 20. American Thyroid Association (ATA) Guidelines Taskforce on Thyroid Nodules and Differentiated Thyroid Cancer. Cooper DS, Doherty GM, Haugen BR, Kloos RT, Lee SL, et al. Revised American Thyroid Association management guidelines for patients with thyroid nodules and differentiated thyroid cancer. Thyroid 2009;19:1167–1214. ArticlePubMed
- 21. Miyauchi A, Ito Y, Oda H. Insights into the management of papillary microcarcinoma of the thyroid. Thyroid 2018;28:23–31. ArticlePubMedPMCPDF
- 22. Ito Y, Miyauchi A, Kihara M, Higashiyama T, Kobayashi K, Miya A. Patient age is significantly related to the progression of papillary microcarcinoma of the thyroid under observation. Thyroid 2014;24:27–34. ArticlePubMedPMCPDF
- 23. Ito Y, Kudo T, Kobayashi K, Miya A, Ichihara K, Miyauchi A. Prognostic factors for recurrence of papillary thyroid carcinoma in the lymph nodes, lung, and bone: analysis of 5,768 patients with average 10-year follow-up. World J Surg 2012;36:1274–1278. ArticlePubMedPDF
- 24. Sugitani I, Toda K, Yamada K, Yamamoto N, Ikenaga M, Fujimoto Y. Three distinctly different kinds of papillary thyroid microcarcinoma should be recognized: our treatment strategies and outcomes. World J Surg 2010;34:1222–1231. ArticlePubMedPDF
- 25. Ito Y, Uruno T, Nakano K, Takamura Y, Miya A, Kobayashi K, et al. An observation trial without surgical treatment in patients with papillary microcarcinoma of the thyroid. Thyroid 2003;13:381–387. ArticlePubMed
- 26. Ito Y, Miyauchi A, Inoue H, Fukushima M, Kihara M, Higashiyama T, et al. An observational trial for papillary thyroid microcarcinoma in Japanese patients. World J Surg 2010;34:28–35. ArticlePubMedPDF
- 27. Brito JP, Ito Y, Miyauchi A, Tuttle RM. A clinical framework to facilitate risk stratification when considering an active surveillance alternative to immediate biopsy and surgery in papillary microcarcinoma. Thyroid 2016;26:144–149. ArticlePubMedPMCPDF
- 28. Tuttle RM, Fagin JA, Minkowitz G, Wong RJ, Roman B, Patel S, et al. Natural history and tumor volume kinetics of papillary thyroid cancers during active surveillance. JAMA Otolaryngol Head Neck Surg 2017;143:1015–1020. ArticlePubMedPMC
- 29. Nixon IJ, Ganly I, Patel SG, Palmer FL, Whitcher MM, Tuttle RM, et al. Thyroid lobectomy for treatment of well differentiated intrathyroid malignancy. Surgery 2012;151:571–579. ArticlePubMed
- 30. Matsuzu K, Sugino K, Masudo K, Nagahama M, Kitagawa W, Shibuya H, et al. Thyroid lobectomy for papillary thyroid cancer: long-term follow-up study of 1,088 cases. World J Surg 2014;38:68–79. ArticlePubMedPDF
- 31. Dionigi G, Chai YJ, Tufano RP, Anuwong A, Kim HY. Transoral endoscopic thyroidectomy via a vestibular approach: why and how? Endocrine 2018;59:275–279. ArticlePubMedPDF
- 32. Adam MA, Thomas S, Youngwirth L, Hyslop T, Reed SD, Scheri RP, et al. Is there a minimum number of thyroidectomies a surgeon should perform to optimize patient outcomes? Ann Surg 2017;265:402–407. ArticlePubMed
- 33. Al-Qurayshi Z, Robins R, Hauch A, Randolph GW, Kandil E. Association of surgeon volume with outcomes and cost savings following thyroidectomy: a national forecast. JAMA Otolaryngol Head Neck Surg 2016;142:32–39. ArticlePubMed
- 34. Youngwirth LM, Adam MA, Scheri RP, Roman SA, Sosa JA. Patients treated at low-volume centers have higher rates of incomplete resection and compromised outcomes: analysis of 31,129 patients with papillary thyroid cancer. Ann Surg Oncol 2016;23:403–409. ArticlePubMedPDF
- 35. Farkas EA, King TA, Bolton JS, Fuhrman GM. A comparison of total thyroidectomy and lobectomy in the treatment of dominant thyroid nodules. Am Surg 2002;68:678–682. ArticlePubMedPDF
- 36. Mancino AT, Kim LT. Chapter 17, Role of radioactive iodine for remnant ablation in patients with papillary thyroid cancer. Management of differentiated thyroid cancer; Cham: Springer; 2017. p. 205–222.
- 37. Dean DS, Hay ID. Prognostic indicators in differentiated thyroid carcinoma. Cancer Control 2000;7:229–239. ArticlePubMedPDF
- 38. Hay ID, Bergstralh EJ, Goellner JR, Ebersold JR, Grant CS. Predicting outcome in papillary thyroid carcinoma: development of a reliable prognostic scoring system in a cohort of 1,779 patients surgically treated at one institution during 1940 through 1989. Surgery 1993;114:1050–1057. PubMed
- 39. Hay ID. Management of patients with low-risk papillary thyroid carcinoma. Endocr Pract 2007;13:521–533. ArticlePubMedPDF
- 40. Lamartina L, Durante C, Filetti S, Cooper DS. Low-risk differentiated thyroid cancer and radioiodine remnant ablation: a systematic review of the literature. J Clin Endocrinol Metab 2015;100:1748–1761. ArticlePubMed
- 41. Sacks W, Fung CH, Chang JT, Waxman A, Braunstein GD. The effectiveness of radioactive iodine for treatment of low-risk thyroid cancer: a systematic analysis of the peer-reviewed literature from 1966 to April 2008. Thyroid 2010;20:1235–1245. ArticlePubMed
- 42. Janovsky CC, Maciel RM, Camacho CP, Padovani RP, Nakabashi CC, Yang JH, et al. A prospective study showing an excellent response of patients with low-risk differentiated thyroid cancer who did not undergo radioiodine remnant ablation after total thyroidectomy. Eur Thyroid J 2016;5:44–49. ArticlePubMedPDF
- 43. Hay ID, Lee R, Morris J, Stan M, Castro M, Fatourechi V, et al. Ultrasound-guided percutaneous ethanol ablation for selected patients with papillary thyroid microcarcinoma: a novel, effective and well tolerated alternative to neck surgery or observation In: 87th Annual Meeting of the American Thyroid Association; 2017 Oct 18–22; Victoria, BC.
- 44. Gazelle GS, Goldberg SN, Solbiati L, Livraghi T. Tumor ablation with radio-frequency energy. Radiology 2000;217:633–646. ArticlePubMed
- 45. Cervelli R, Mazzeo S, De Napoli L, Boccuzzi A, Pontillo-Contillo B, Materazzi G, et al. Radiofrequency ablation in the treatment of benign thyroid nodules: an efficient and safe alternative to surgery. J Vasc Interv Radiol 2017;28:1400–1408. ArticlePubMed
- 46. Cheng Z, Che Y, Yu S, Wang S, Teng D, Xu H, et al. US-guided percutaneous radiofrequency versus microwave ablation for benign thyroid nodules: a prospective multicenter study. Sci Rep 2017;7:9554. ArticlePubMedPMC
- 47. Radzina M, Cantisani V, Rauda M, Nielsen MB, Ewertsen C, D'Ambrosio F, et al. Update on the role of ultrasound guided radiofrequency ablation for thyroid nodule treatment. Int J Surg 2017;41(Suppl 1):S82–S93. ArticlePubMed
- 48. Cesareo R, Palermo A, Pasqualini V, Cianni R, Gaspa G, Manfrini S, et al. Radiofrequency ablation for the management of thyroid nodules: a critical appraisal of the literature. Clin Endocrinol (Oxf) 2017;87:639–648. ArticlePubMedPDF
- 49. Zhao Q, Tian G, Kong D, Jiang T. Meta-analysis of radiofrequency ablation for treating the local recurrence of thyroid cancers. J Endocrinol Invest 2016;39:909–916. ArticlePubMedPDF
- 50. Jeong SY, Baek JH, Choi YJ, Chung SR, Sung TY, Kim WG, et al. Radiofrequency ablation of primary thyroid carcinoma: efficacy according to the types of thyroid carcinoma. Int J Hyperthermia 2018 1 24 [Epub]. Article
- 51. Sun J, Liu X, Zhang Q, Hong Y, Song B, Teng X, et al. Papillary thyroid carcinoma treated with radiofrequency ablation in a patient with hypertrophic cardiomyopathy: a case report. Korean J Radiol 2016;17:558–561. ArticlePubMedPMCPDF
- 52. Zhang M, Luo Y, Zhang Y, Tang J. Efficacy and safety of ultrasound-guided radiofrequency ablation for treating low-risk papillary thyroid microcarcinoma: a prospective study. Thyroid 2016;26:1581–1587. ArticlePubMed
- 53. Papini E, Guglielmi R, Gharib H, Misischi I, Graziano F, Chianelli M, et al. Ultrasound-guided laser ablation of incidental papillary thyroid microcarcinoma: a potential therapeutic approach in patients at surgical risk. Thyroid 2011;21:917–920. ArticlePubMedPMC
- 54. Valcavi R, Piana S, Bortolan GS, Lai R, Barbieri V, Negro R. Ultrasound-guided percutaneous laser ablation of papillary thyroid microcarcinoma: a feasibility study on three cases with pathological and immunohistochemical evaluation. Thyroid 2013;23:1578–1582. ArticlePubMedPDF
- 55. Zhou W, Jiang S, Zhan W, Zhou J, Xu S, Zhang L. Ultrasound-guided percutaneous laser ablation of unifocal T1N0M0 papillary thyroid microcarcinoma: preliminary results. Eur Radiol 2017;27:2934–2940. ArticlePubMedPDF
References
ATA 2009 Risk Stratification System with Proposed Modifications for Structural Disease Recurrence in Differentiated Thyroid Cancer
Adapted from Haugen et al. [7].
ATA, American Thyroid Association; PTC, papillary thyroid cancer; DM, distant metastases; RAI, radioactive iodine; WBS, whole body scan; N0, no evidence of regional lymph node metastasis; N1, metastasis to regional node; EFVPTC, encapsulated follicular variant of papillary thyroid cancer; WD-FTC, well differentiated follicular thyroid cancer; PMC, papillary microcarcinoma; ETE, extrathyroidal extension; LN, lymph nodes; Gross ETE, macroscopic invasion of tumor into the perithyroidal soft tissues; FTC, follicular thyroid cancer.
The Expanded Definition of Low-Risk Thyroid Cancer
| Previous features of low-risk thyroid cancer [20] | New features of low-risk thyroid cancer [79] |
|---|---|
| Low-risk for recurrence | Low-risk for recurrence |
| PTC with all of the following: | All previous features of low-risk for recurrence PTC |
| No local or DM | PTC with: clinical N0 or ≤5 pathologic N1 micro-metastases (<0.2 cm in largest dimension) |
| All macroscopic tumor has been resected | Intra-thyroidal EFVPTC |
| No tumor invasion of loco-regional tissues or structures | Intra-thyroidal WD-FTC with capsular invasion and no or minimal (<4 foci) vascular invasion |
| No aggressive cyto-type (e.g., tall cell, hobnail variant, columnar cell carcinoma) | Intra-thyroidal PMC, unifocal or multifocal, including BRAFV600E mutated (if known) |
| If RAI given, there are no RAI-avid metastatic foci outside the thyroid bed on the first post treatment WBS | Low-risk for mortality |
| No vascular invasion | Age cut-off <55 years of age at diagnosis |
| Minor ETE detected only on histological examination has no impact on either T category or overall stage | |
| T3a tumors >4 cm confined to the thyroid gland, any N, M0 | |
| T3b tumor of any size with gross ETE into strap muscles only (sternohyoid, sternothyroid, thyrohyoid, or omohyoid muscles), any N, M0 | |
| Very low-risk tumors | |
| PMC with no evidence of ETE nor metastases |
T3 tumors, >4 cm limited to the thyroid, or gross ETE invading only strap muscles (Stage II).
PTC, papillary thyroid cancer; DM, distant metastases; RAI, radioactive iodine; WBS, whole body scan; N0, no evidence of regional lymph node metastasis; N1, metastasis to regional node; EFVPTC, encapsulated follicular variant of papillary thyroid cancer; WD-FTC, well differentiated follicular thyroid cancer; PMC, papillary microcarcinoma; ETE, extrathyroidal extension; M0, no distant metastasis.
Clinical Framework: Risk Stratification Approach to Decision Making in Probable or Proven Papillary Microcarcinoma
Adapted from Brito et al. [27].
US, ultrasound/ultrasonographic; ETE, extrathyroidal extension; cN0, clinically no lymph node; cM0, clinically no distant metastasis; FU, follow-up; PMC, papillary microcarcinoma; RLN, recurrent laryngeal nerve; LN, lymph node; FDG, fluorodeoxyglucose; FH, family history; FNA, fine needle aspiration; N1, metastasis to regional node; M1, distant metastasis; PTC, papillary thyroid cancer; TC, thyroid cancer.
Active Surveillance Studies
| Japan: Ito et al. (2014) [22] | Japan: Sugitani et al. (2010) [24] | USA: Tuttle et al. (2017) [28] | |
|---|---|---|---|
| No. of patients | 1,235 | 230 Patients and 300 lesions | 291 |
| Tumor size cut-off, cm | ≤1 | ≤1 | ≤1.5 |
| Time of follow-up | Mean, 6.25 years (range, 1.5–18.91) | Mean, 5 years (range, 1–17) | Median, 25 months (range, 6–166) |
| At 10 year observation | |||
| Ultrasound surveillance | 1–2/year | 1–2/year | 2/year for 2 years then 1/year |
| Tumor increase by ≥3 mm, % | 8 | 7 | 3.8 |
| Novel lymph node metastases, % | 3.8 | 1 | 0 |
Figure & Data
References
Citations

- Radiofrequency Ablation for Primary Thyroid Cancer
Iram Hussain
Endocrine Practice.2026;[Epub] CrossRef - Clinical and surgical outcome of hemi thyroidectomy in low-risk papillary carcinoma thyroid
Muhammad Ali Azad, A. K. M. Mashiul Munir, Mohammad Misbah Al Kabir Sumon, Lailanur, Mohammad Nesar Uddin
International Surgery Journal.2025; 12(5): 713. CrossRef - Thermal field management in thyroid ablation for papillary thyroid carcinoma: Advancing precision and patient-centered care
Sivan Sathish
World Journal of Radiology.2025;[Epub] CrossRef - Risk of malignancy in Thy3 thyroid nodules
Emad Mofid Nassif Rezkallah, Ragai Sobhi Hanna, Wael Magdy Elsaify
Endocrine Regulations.2024; 58(1): 19. CrossRef - Adequacy of clinical guideline recommendations for patients with low-risk cancer managed with monitoring: systematic review
Kiana K. Collins, Claire Friedemann Smith, Tori Ford, Nia Roberts, Brian D. Nicholson, Jason L. Oke
Journal of Clinical Epidemiology.2024; 169: 111280. CrossRef - Endokrine Onkologie
Kerstin Lorenz
Die Innere Medizin.2024; 65(7): 656. CrossRef - Racial–Ethnic Comparison of Treatment for Papillary Thyroid Cancer in the Military Health System
Yvonne L. Eaglehouse, Sarah Darmon, Craig D. Shriver, Kangmin Zhu
Annals of Surgical Oncology.2024; 31(12): 8196. CrossRef - A Qualitative Thematic Analysis Exploring Chinese Young Adults’ Experiences in Decision Making on the Management of Low-Risk Papillary Thyroid Cancer
Xinyue Gu, Pingting Zhu, Hui Zhang, Wen Wang, Yinwen Ding, Meiyan Qian, Guanghui Shi, Qianqian Zhang, Josephine Hegarty
Thyroid®.2024; 34(12): 1486. CrossRef - Safety and Effectiveness of Percutaneous Ethanol Injection as a Treatment for Locally Recurrent Papillary Thyroid Carcinoma
Amin Momeni Moghaddam, Mahsa Abbaszadeh, Vajihe Chavoshi, Amir Ebadinejad, Nafiseh Hassanloo, Farhad Hosseinpanah
International Journal of Endocrinology and Metabolism.2024;[Epub] CrossRef - Integrated metabolic and genetic analysis reveals distinct features of human differentiated thyroid cancer
Eduardo Cararo Lopes, Akshada Sawant, Dirk Moore, Hua Ke, Fuqian Shi, Saurabh Laddha, Ying Chen, Anchal Sharma, Jake Naumann, Jessie Yanxiang Guo, Maria Gomez, Maria Ibrahim, Tracey L. Smith, Gregory M. Riedlinger, Edmund C. Lattime, Stanley Trooskin, Shr
Clinical and Translational Medicine.2023;[Epub] CrossRef - Clinical management of low-risk papillary thyroid microcarcinoma
Chie MASAKI, Kiminori SUGINO, Koichi ITO
Minerva Endocrinology.2022;[Epub] CrossRef - The circ_FAM53B-miR-183-5p-CCDC6 axis modulates the malignant behaviors of papillary thyroid carcinoma cells
Chong Zhang, Huxia Gu, Dingrong Liu, Fuyun Tong, Huijie Wei, Dan Zhou, Jing Fang, Xiaolu Dai, Haibo Tian
Molecular and Cellular Biochemistry.2022; 477(11): 2627. CrossRef - An Appraisal and Update of Fluorodeoxyglucose and Non-Fluorodeoxyglucose-PET Tracers in Thyroid and Non–Thyroid Endocrine Neoplasms
Aadil Adnan, Shobhana Raju, Rakesh Kumar, Sandip Basu
PET Clinics.2022; 17(3): 343. CrossRef - A Narrative Review of Preventive Central Lymph Node Dissection in Patients With Papillary Thyroid Cancer - A Necessity or an Excess
David D. Dolidze, Alexey V. Shabunin, Robert B. Mumladze, Arshak V. Vardanyan, Serghei D. Covantsev, Alexander M. Shulutko, Vasiliy I. Semikov, Khalid M. Isaev, Airazat M. Kazaryan
Frontiers in Oncology.2022;[Epub] CrossRef - Ethanol Ablation as a Treatment in a Low-Risk Follicular Thyroid Cancer: A Case Report
Juan Pesantez, Carla Lituma, Carla Valencia, Jose Prieto, Marco Cazorla
Cureus.2022;[Epub] CrossRef - The new T3b category has clinical significance? SEER‐based study
Jingzhe Xiang, Zhihong Wang, Wei Sun, Hao Zhang
Clinical Endocrinology.2021; 94(3): 449. CrossRef - Efficacy and Safety of Thermal Ablation for Solitary T1bN0M0 Papillary Thyroid Carcinoma: A Multicenter Study
Xiao-Jing Cao, Juan Liu, Ya-Lin Zhu, Lu Qi, Geng Liu, Hong-Ling Wang, Zhong-Hua Wang, Ying Zhou, Jun-Feng He, Jian-Qin Guo, Li-Li Shi, Mei Jian, Aini Shataer, Guo-Zhen Yan, Zhen-Long Zhao, Ying Wei, Li-Li Peng, Yan Li, Ying Che, Shu-Rong Wang, Ming-An Yu
The Journal of Clinical Endocrinology & Metabolism.2021; 106(2): e573. CrossRef - A Clinical Audit of Hemithyroidectomy for Differentiated Thyroid Cancer—Experience from a Tertiary Cancer Center
Nithyanand Chidambaranathan, Shivakumar Thiagarajan, Nandini Menon, Adhara Chakraborthy, Richa Vaish, Devendra Chaukar
Indian Journal of Surgery.2021; 83(6): 1444. CrossRef - Pros and cons of hemi‐thyroidectomy for low‐risk differentiated thyroid cancer
Alexander J. Papachristos, Anthony Glover, Mark S. Sywak, Stan B. Sidhu
ANZ Journal of Surgery.2021; 91(9): 1704. CrossRef - Lactate Dehydrogenase A as a Potential New Biomarker for Thyroid Cancer
Eun Jeong Ban, Daham Kim, Jin Kyong Kim, Sang-Wook Kang, Jandee Lee, Jong Ju Jeong, Kee-Hyun Nam, Woong Youn Chung, Kunhong Kim
Endocrinology and Metabolism.2021; 36(1): 96. CrossRef - Taraxasterol inhibits TGF-β1-induced epithelial-to-mesenchymal transition in papillary thyroid cancer cells through regulating the Wnt/β-catenin signaling
J Zhu, X Li, S Zhang, J Liu, X Yao, Q Zhao, B Kou, P Han, X Wang, Y Bai, Z Zheng, C Xu
Human & Experimental Toxicology.2021; 40(12_suppl): S87. CrossRef - Is Delayed Papillary Thyroid Cancer Surgery Associated with Higher Mortality Risk?
Eddy P. Lincango Naranjo, Juan P. Brito
Clinical Thyroidology.2021; 33(9): 400. CrossRef - MicroRNA-99a-3p/GRP94 axis affects metastatic progression of human papillary thyroid carcinoma by regulating ITGA2 expression and localization
Yun Gao, Yi Pan, Tingting Wang, Ying Yao, Wenbo Yuan, Xue Zhu, Ke Wang
Acta Biochimica et Biophysica Sinica.2021; 53(12): 1650. CrossRef - Microscopic Extrathyroidal Extension Results in Increased Rate of Tumor Recurrence and Is an Independent Predictor of Patient’s Outcome in Middle Eastern Papillary Thyroid Carcinoma
Sandeep Kumar Parvathareddy, Abdul K. Siraj, Zeeshan Qadri, Felisa DeVera, Khawar Siddiqui, Saif S. Al-Sobhi, Fouad Al-Dayel, Khawla S. Al-Kuraya
Frontiers in Oncology.2021;[Epub] CrossRef - 80MAP17 promotes the tumorigenesis of papillary thyroid carcinoma by reducing the stability of p53
Kun Yu, Hongjiang Lu, Yanhong Chen, Ying Xin, Zhuo Tan, Qiong Yang
Frontiers in Bioscience-Landmark.2021;[Epub] CrossRef - New paradigms in the treatment of low-risk thyroid cancer
Firas Baidoun, Anas M. Saad, Omar Abdel-Rahman
Expert Review of Endocrinology & Metabolism.2020; 15(4): 251. CrossRef - The Impact of Transcription Factor Prospero Homeobox 1 on the Regulation of Thyroid Cancer Malignancy
Magdalena Rudzińska, Barbara Czarnocka
International Journal of Molecular Sciences.2020; 21(9): 3220. CrossRef - Modified risk stratification based on cervical lymph node metastases following lobectomy for papillary thyroid carcinoma
Eyun Song, Jonghwa Ahn, Dong Eun Song, Won Woong Kim, Min Ji Jeon, Tae‐Yon Sung, Tae Yong Kim, Ki Wook Chung, Won Bae Kim, Young Kee Shong, Suck Joon Hong, Yu‐Mi Lee, Won Gu Kim
Clinical Endocrinology.2020; 92(4): 358. CrossRef - Clinicopathological significance of the single nucleotide polymorphism, rs2853669 within the TERT promoter in papillary thyroid carcinoma
Tatsuya Hirokawa, Yuu Arimasu, Tomohiro Chiba, Masachika Fujiwara, Hiroshi Kamma
Pathology International.2020; 70(4): 217. CrossRef - Diagnostic accuracy and ability to reduce unnecessary FNAC: A comparison between four Thyroid Imaging Reporting Data System (TI-RADS) versions
Lingsze Tan, Ying Sern Tan, Suzet Tan
Clinical Imaging.2020; 65: 133. CrossRef - Amino Acid Transporters as Potential Therapeutic Targets in Thyroid Cancer
Keisuke Enomoto, Muneki Hotomi
Endocrinology and Metabolism.2020; 35(2): 227. CrossRef - FDG PET/CT versus somatostatin receptor PET/CT in TENIS syndrome: a systematic review and meta-analysis
Felipe Alves Mourato, Maria Amorim Almeida, Ana Emília Teixeira Brito, Aline Lopes Garcia Leal, Paulo Almeida Filho, Elba Etchebehere
Clinical and Translational Imaging.2020; 8(5): 365. CrossRef - Factors Associated with Health Behaviors in Thyroid Cancer Survivors
Junghyun Yoon, Boyoung Park
Journal of Cancer Prevention.2020; 25(3): 173. CrossRef - Patient-Derived Papillary Thyroid Cancer Organoids for Radioactive Iodine Refractory Screening
Luc H.J. Sondorp, Vivian M.L. Ogundipe, Andries H. Groen, Wendy Kelder, Annelies Kemper, Thera P. Links, Robert P. Coppes, Schelto Kruijff
Cancers.2020; 12(11): 3212. CrossRef - Hemithyroidectomy for Thyroid Cancer: A Review
Noor Addasi, Abbey Fingeret, Whitney Goldner
Medicina.2020; 56(11): 586. CrossRef - Clinical Outcomes after Early and Delayed Radioiodine Remnant Ablation in Patients with Low-Risk Papillary Thyroid Carcinoma: Propensity Score Matching Analysis
Jonghwa Ahn, Meihua Jin, Eyun Song, Min Ji Jeon, Tae Yong Kim, Jin-Sook Ryu, Won Bae Kim, Young Kee Shong, Ji Min Han, Won Gu Kim
Endocrinology and Metabolism.2020; 35(4): 830. CrossRef - Clinical Significance of Gross Invasion of Strap Muscles in Patients With 1- to 4-cm-Sized Papillary Thyroid Carcinoma Undergoing Lobectomy
Eyun Song, Won Woong Kim, Min Ji Jeon, Tae-Yon Sung, Dong Eun Song, Tae Yong Kim, Ki Wook Chung, Won Bae Kim, Young Kee Shong, Suck Joon Hong, Yu-Mi Lee, Won Gu Kim
Annals of Surgical Oncology.2019; 26(13): 4466. CrossRef - Lobectomy Is Feasible for 1–4 cm Papillary Thyroid Carcinomas: A 10-Year Propensity Score Matched-Pair Analysis on Recurrence
Eyun Song, Minkyu Han, Hye-Seon Oh, Won Woong Kim, Min Ji Jeon, Yu-Mi Lee, Tae Yong Kim, Ki Wook Chung, Won Bae Kim, Young Kee Shong, Suck Joon Hong, Tae-Yon Sung, Won Gu Kim
Thyroid.2019; 29(1): 64. CrossRef - Laser and radiofrequency ablations for benign and malignant thyroid tumors
Giovanni Mauri, Nicolò Gennaro, Min Kyoung Lee, Jung Hwan Baek
International Journal of Hyperthermia.2019; 36(2): 13. CrossRef - US-Guided Radiofrequency Ablation for Low-Risk Papillary Thyroid Microcarcinoma: Efficacy and Safety in a Large Population
Hyun Kyung Lim, Se Jin Cho, Jung Hwan Baek, Kang Dae Lee, Chang Woo Son, Jung Min Son, Seon Mi Baek
Korean Journal of Radiology.2019; 20(12): 1653. CrossRef - Utility of Early Postoperative Unstimulated Thyroglobulin in Influencing Decision Making in Patients with Papillary Thyroid Carcinoma
Alexandria D. McDow, Cynthia M. Shumway, Susan C. Pitt, David F. Schneider, Rebecca S. Sippel, Kristin L. Long
Annals of Surgical Oncology.2019; 26(12): 4002. CrossRef - Extent of Surgery for Low-Risk Differentiated Thyroid Cancer
Alexandria D. McDow, Susan C. Pitt
Surgical Clinics of North America.2019; 99(4): 599. CrossRef
 PubReader
 ePub Link
 Cite
 XML Download

Fig. 1
| ATA low-risk | ATA intermediate risk | ATA high risk |
|---|---|---|
| PTC with all of the following: | Microscopic ETE | Gross ETE |
| No local or DM | RAI-avid metastatic foci in the neck on the first post-treatment WBS | Incomplete tumor resection |
| All macroscopic tumor has been resected | Aggressive cyto-type (e.g., tall cell, hobnail variant, columnar cell carcinoma) | Distant metastases |
| No tumor invasion of loco-regional tissues or structures | PTC with vascular invasion | Postoperative serum thyroglobulin suggestive of DM |
| No aggressive cyto-type (e.g., tall cell, hobnail variant, columnar cell carcinoma) | Clinical N1 or >5 pathologic N1 with all involved LN <3 cm in largest dimension | Pathologic N1 with any metastatic LN ≥3 cm in largest dimension |
| If RAI given, there are no RAI-avid metastatic foci outside the thyroid bed on the first post treatment WBS | Multifocal PMC with ETE and BRAFV600E mutated (if known) | FTC with extensive vascular invasion (>4 foci of vascular invasion) |
| No vascular invasion | ||
| Clinical N0 or ≤5 pathologic N1 micro-metastases (<0.2 cm in largest dimension) | ||
| Intra-thyroidal EFVPTC | ||
| Intra-thyroidal WD-FTC with capsular invasion and no or minimal (<4 foci) vascular invasion | ||
| Intra-thyroidal PMC, unifocal or multifocal, including BRAFV600E mutated (if known) |
| Previous features of low-risk thyroid cancer [ | New features of low-risk thyroid cancer [ |
|---|---|
| Low-risk for recurrence | Low-risk for recurrence |
| PTC with all of the following: | All previous features of low-risk for recurrence PTC |
| No local or DM | PTC with: clinical N0 or ≤5 pathologic N1 micro-metastases (<0.2 cm in largest dimension) |
| All macroscopic tumor has been resected | Intra-thyroidal EFVPTC |
| No tumor invasion of loco-regional tissues or structures | Intra-thyroidal WD-FTC with capsular invasion and no or minimal (<4 foci) vascular invasion |
| No aggressive cyto-type (e.g., tall cell, hobnail variant, columnar cell carcinoma) | Intra-thyroidal PMC, unifocal or multifocal, including BRAFV600E mutated (if known) |
| If RAI given, there are no RAI-avid metastatic foci outside the thyroid bed on the first post treatment WBS | Low-risk for mortality |
| No vascular invasion | Age cut-off <55 years of age at diagnosis |
| Minor ETE detected only on histological examination has no impact on either T category or overall stage | |
| T3a tumors >4 cm confined to the thyroid gland, any N, M0 | |
| T3b tumor of any size with gross ETE into strap muscles only (sternohyoid, sternothyroid, thyrohyoid, or omohyoid muscles), any N, M0 | |
| Very low-risk tumors | |
| PMC with no evidence of ETE nor metastases |
| Candidates for observation | Tumor and neck US findings | Patient features | Medical team features |
|---|---|---|---|
| Ideal | Single thyroid nodule Well-defined margins | Older individuals (<60 years) | Experienced multidisciplinary team |
| Surrounded by 2+ mm of normal thyroid parenchyma | Willing to accept an active surveillance approach | High-quality neck US performed by skilled radiologist | |
| No evidence of ETE | Understands that a surgical intervention might be necessary in the future | Prospective data collection | |
| Previous US with stability | Expected to be compliant with FU plans | Tracking or reminder program to ensure proper FU | |
| cN0 | Supportive significant others | ||
| cM0 | Life-threatening comorbidities | ||
| Appropriate | Multifocal PMC | Young adults and middle-aged patients (18–59 years) | Experienced endocrinologist or thyroid surgeon |
| Subcapsular locations not adjacent to RLN without evidence of ETE | Strong FH of PTC | Neck US routinely available | |
| Ill-defined margins | Child bearing potential | ||
| Background US findings that will make FU difficult (thyroiditis, nonspecific LNs, multiple, other benign-appearing thyroid nodules) | |||
| FDG avid PMC | |||
| Inappropriate | Evidence of aggressive cytology on FNA (rare) | Children and adolescents (<18 years of age) | Reliable neck US not available |
| Subcapsular locations adjacent to RLN | Unlikely to be compliant with FU plans | Little experience with TC management | |
| Evidence of ETE | Not willing to accept an observation approach | ||
| Clinical evidence of invasion of RLN or trachea (rare) | |||
| N1 disease at initial evaluation or identified during FU | |||
| M1 disease (very rare) | |||
| Definitive increase in size of ≥3 mm in a confirmed PTC tumor |
| Japan: Ito et al. (2014) [ | Japan: Sugitani et al. (2010) [ | USA: Tuttle et al. (2017) [ | |
|---|---|---|---|
| No. of patients | 1,235 | 230 Patients and 300 lesions | 291 |
| Tumor size cut-off, cm | ≤1 | ≤1 | ≤1.5 |
| Time of follow-up | Mean, 6.25 years (range, 1.5–18.91) | Mean, 5 years (range, 1–17) | Median, 25 months (range, 6–166) |
| At 10 year observation | |||
| Ultrasound surveillance | 1–2/year | 1–2/year | 2/year for 2 years then 1/year |
| Tumor increase by ≥3 mm, % | 8 | 7 | 3.8 |
| Novel lymph node metastases, % | 3.8 | 1 | 0 |
Adapted from Haugen et al. [ ATA, American Thyroid Association; PTC, papillary thyroid cancer; DM, distant metastases; RAI, radioactive iodine; WBS, whole body scan; N0, no evidence of regional lymph node metastasis; N1, metastasis to regional node; EFVPTC, encapsulated follicular variant of papillary thyroid cancer; WD-FTC, well differentiated follicular thyroid cancer; PMC, papillary microcarcinoma; ETE, extrathyroidal extension; LN, lymph nodes; Gross ETE, macroscopic invasion of tumor into the perithyroidal soft tissues; FTC, follicular thyroid cancer.
T3 tumors, >4 cm limited to the thyroid, or gross ETE invading only strap muscles (Stage II). PTC, papillary thyroid cancer; DM, distant metastases; RAI, radioactive iodine; WBS, whole body scan; N0, no evidence of regional lymph node metastasis; N1, metastasis to regional node; EFVPTC, encapsulated follicular variant of papillary thyroid cancer; WD-FTC, well differentiated follicular thyroid cancer; PMC, papillary microcarcinoma; ETE, extrathyroidal extension; M0, no distant metastasis.
Adapted from Brito et al. [ US, ultrasound/ultrasonographic; ETE, extrathyroidal extension; cN0, clinically no lymph node; cM0, clinically no distant metastasis; FU, follow-up; PMC, papillary microcarcinoma; RLN, recurrent laryngeal nerve; LN, lymph node; FDG, fluorodeoxyglucose; FH, family history; FNA, fine needle aspiration; N1, metastasis to regional node; M1, distant metastasis; PTC, papillary thyroid cancer; TC, thyroid cancer.


