
 KES

Articles
- Page Path
- HOME > Endocrinol Metab > Volume 38(4); 2023 > Article
-
Review ArticleAdrenal Gland Recent Updates on the Management of Adrenal Incidentalomas
 Keypoint
The 2023 European Society of Endocrinology guideline offers updated protocols for adrenal incidentalomas. Key points include recognizing post-dexamethasone cortisol levels above 50 nmol/L as mild autonomous cortisol secretion and not requiring further follow-up for adrenal masses with ≤10 Hounsfield units on non-contrast CT. The guideline emphasizes steroid metabolomics, the importance of specialized surgeons, a team approach for uncertain masses, and proactive surgical intervention for young and pregnant patients, highlighting the evolving landscape of adrenal incidentaloma management. -
Seung Shin Park
 , Jung Hee Kim
-
Endocrinology and Metabolism 2023;38(4):373-380.
DOI: https://doi.org/10.3803/EnM.2023.1779
Published online: August 16, 2023
Department of Internal Medicine, Seoul National University Hospital, Seoul National University College of Medicine, Seoul, Korea
- Corresponding author: Jung Hee Kim. Department of Internal Medicine, Seoul National University Hospital, Seoul National University College of Medicine, 101 Daehak-ro, Jongno-gu, Seoul 03080, Korea Tel: +82-2-2072-4839, Fax: +82-2-764-2199, E-mail: jhee1@snu.ac.kr
Copyright © 2023 Korean Endocrine Society
This is an Open Access article distributed under the terms of the Creative Commons Attribution Non-Commercial License (http://creativecommons.org/licenses/by-nc/4.0/) which permits unrestricted non-commercial use, distribution, and reproduction in any medium, provided the original work is properly cited.


Figure & Data
References
Citations

- The Relationship Between Bone Health Status of Post-Menopausal Women with Non-Functional Adrenal Tumours/Mild Autonomous Cortisol Secretion and Their Baseline Morning Adrenocorticotropic Level
Alexandra-Ioana Trandafir, Oana-Claudia Sima, Nina Ionovici, Dana Manda, Mihai Costachescu, Mara Carsote
Diagnostics.2026; 16(2): 180. CrossRef - Assessing the informatics utility of artificial intelligence chatbots for patient and clinician support: the case of adrenal incidentaloma
Nergis Basmaci, Seren Aksun, Bulent Okan Yildiz
Endocrine.2026;[Epub] CrossRef - SAGE-DM—Senescence-Associated Gluco-Endocrinopathy Diabetes Mellitus: comprehensive review
Michał Szklarz, Katarzyna Wołos-Kłosowicz, Julia Modzelewska, Jan Górny, Robert Modzelewski, Wojciech Matuszewski
European Journal of Medical Research.2026;[Epub] CrossRef - Predictive Model for Mild Autonomous Cortisol Secretion in Patients Evaluated in Artificial Intelligence–Driven Adrenal Incidentaloma Clinic
Mehmet Kostek, Chandler McLeod, Julia Kasmirski, Haleigh Negrete, Srini Tridandapani, Micah Cochran, John D Osborne, Andrea Gillis, Herbert Chen, Brenessa Lindeman
Journal of the American College of Surgeons.2026; 242(5): 1290. CrossRef - Plasma proteomic profiling identifies apolipoprotein A4 as a downregulated biomarker of adrenocortical carcinoma: a multi-platform discovery and validation study
Seung Shin Park, Hoseok Seo, Sun Joon Moon, Han Na Jang, Seung Hun Lee, Su-jin Kim, Kyu Eun Lee, Dohyun Han, Jung Hee Kim
European Journal of Endocrinology.2026; 194(5): 641. CrossRef - AI-enabled precision evaluation of adrenal masses: radiomics, deep learning, and explainable imaging biomarkers
Chaohui Liang, Hao Zhu
Frontiers in Endocrinology.2026;[Epub] CrossRef - A deep learning algorithm for automated adrenal gland segmentation on non-contrast CT images
Fanxing Meng, Tuo Zhang, Yukun Pan, Xiaojing Kan, Yuwei Xia, Mengyuan Xu, Jin Cai, Fangbin Liu, Yinghui Ge
BMC Medical Imaging.2025;[Epub] CrossRef - A Secret Revealed: The Coexistence of a Pheochromocytoma and Independent Adrenocorticotropic Hormone-Secreting Cushing Syndrome Within the Same Adrenal Gland
Sana Rafi, Meryam Alahyane, Ghizlane Elmghari, Nawal El Ansari, Fatim Zahra Hazmiri, Oumayma Ait Ouhssain, Hanane Rais
Cureus.2025;[Epub] CrossRef - The Landmark Series: Evaluation and Management of Adrenal Incidentalomas
Lily Owei, Heather Wachtel
Annals of Surgical Oncology.2025; 32(7): 4712. CrossRef - Management of adrenal incidentalomas: who, why and how?
Marta Araujo-Castro, María Bernarda Iriarte-Durán, Paola Parra-Ramírez, Sara Donato
Current Opinion in Endocrinology, Diabetes & Obesity.2025; 32(5): 210. CrossRef - Changing paradigms in evaluating adrenal incidentalomas: Bayesian evaluation of [18F]Fluorodeoxyglucose positron emission tomography use, honed on adrenocortical carcinoma
Ioannis Ilias, Georgios Meristoudis
World Journal of Clinical Oncology.2025;[Epub] CrossRef - Imaging in endocrinology
Ines Harper, Ashley S Shaw, HK Cheow
Medicine.2025; 53(9): 559. CrossRef - Efficiency of Microwave Ablation for Cortisol-Producing Adrenal Adenomas: Case Series and a Literature Review
Alicija Krasavceva, Juozas Jarašūnas, Donatas Jocius, Romena Laukienė, Žydrūnė Visockienė, Virgilijus Beiša
Acta medica Lituanica.2025; 32(2): 5. CrossRef - Machine learning-based classification of adrenal tumors using clinical, hormonal, and body composition data
Seung Shin Park, Jongsung Noh, Jinhee Kim, Taesung Kim, Hae Jin Seo, Chang Ho Ahn, Jaegul Choo, Man Ho Choi, Jung Hee Kim
European Journal of Endocrinology.2025; 193(2): 204. CrossRef - Clinical and genetic features of older patients with pheochromocytomas and paragangliomas: A multicenter retrospective study
Xiaowen Xu, Yingjie Shen, Jingjing Jiang, Yingxian Pang, Kai Cheng, Zhi Li, Yizhou Wang, Junjie Chen, Anze Yu, Jing Wang, Minghao Li, Jing Zhang, Longfei Liu
Journal of Endocrinological Investigation.2025; 49(1): 81. CrossRef - Dexamethasone Suppression Testing in Patients with Adrenal Incidentalomas with/Without Mild Autonomous Cortisol Secretion: Spectrum of Cortisol Cutoffs and Additional Assays (An Updated Analysis)
Alexandra-Ioana Trandafir, Mara Carsote
Biomedicines.2025; 13(9): 2169. CrossRef - Update of the guidelines on the management of adrenal incidentaloma from the adrenal group of the Spanish society of endocrinology and nutrition (SEEN)
Marta Araujo-Castro, María Calatayud Gutiérrez, Paola Parra Ramírez, Edelmiro Menéndez Torre, Paz de Miguel, Miguel Paja, Miguel Ángel Mangas, Cristina Lamas Oliveira, Felicia Alexandra Hanzu
Endocrine.2025; 90(2): 453. CrossRef - Morpho-Functional and Biochemical Characterization of Adrenal Masses in a Heterogeneous Cancer Population
Rosaria Meucci, Antonio Stigliano, Giuseppe Campagna, Francesco Garaci, Tommaso Pintus, Guido Roberto, Alberto Signore
Cancers.2025; 17(17): 2897. CrossRef - Mineral Metabolism Assays, Central DXA, and Fracture Risk Probabilities in Menopausal Patients with Non-Functional Adrenal Tumors with/Without Mild Autonomous Cortisol Secretion: Does the Presence of Unilateral Versus Bilateral Tumors Matter?
Alexandra-Ioana Trandafir, Mara Carsote, Mihai Costachescu, Oana-Claudia Sima, Alexandru-Florin Florescu
Life.2025; 15(10): 1639. CrossRef - The diagnostic value of native and early post-contrast CT attenuation in differentiating benign from potentially malignant adrenal lesions
Haris Đug, Davor Ivanić, Faris Tursić, Ivana Čerkez, Samir Delibegović
International Urology and Nephrology.2025; 58(5): 1727. CrossRef - Feocromocitoma: clasificación molecular en grupos con diferente fenotipo bioquímico noradrenérgico y riesgo de metástasis [Pheochromocytoma: molecular classification into groups with different noradrenergic biochemical phenotypes and risk of metastasis]
Dayana Aracely León-Pallasco, Sebastián Oswaldo Paredes-Tobar, Elio Joel Palma-Coque, Olivia Elizabeth Altamirano-Guerrero
Cuaderno de enfermería. Revista científica.2025; 3(especial2): 165. CrossRef - Adrenal Incidentalomas: Diagnostic, Etiological and Therapeutic Aspects
Malak Riznat, Jade Issouani, Mohamed Malad, Hajar Srifi, Ahmed Anas Guerboub
Open Journal of Endocrine and Metabolic Diseases.2025; 15(08): 133. CrossRef - Personalized Management of Malignant and Non-Malignant Ectopic Mediastinal Thyroid: A Proposed 10-Item Algorithm Approach
Mara Carsote, Mihai-Lucian Ciobica, Oana-Claudia Sima, Adrian Ciuche, Ovidiu Popa-Velea, Mihaela Stanciu, Florina Ligia Popa, Claudiu Nistor
Cancers.2024; 16(10): 1868. CrossRef - Temporal trends in clinical features of patients with primary aldosteronism over 20 years
Seung Shin Park, Chang Ho Ahn, Sang Wan Kim, Jung-Min Koh, Seung Hun Lee, Jung Hee Kim
Hypertension Research.2024; 47(8): 2019. CrossRef - Steroid Profiling in the Differential Diagnosis of Cushing's Syndrome and Diagnosis of MACS
A. Nankova, T. Kamenova, V. Vasilev, At. Elenkova, D. Svinarov, G. Kirilov, S. Zaharieva
Acta Medica Bulgarica.2024; 51(2): 1. CrossRef - Adrenal incidentalomas
Ivana Ságová
Vnitřní lékařství.2024; 70(5): E9. CrossRef - Ectopic Mediastinal Thyroid: A Crossroad Between a Multi-Layered Endocrine Perspective and a Contemporary Approach in Thoracic Surgery
Claudiu Nistor, Mihai-Lucian Ciobica, Oana-Claudia Sima, Anca-Pati Cucu, Florina Vasilescu, Lucian-George Eftimie, Dana Terzea, Mihai Costachescu, Adrian Ciuche, Mara Carsote
Life.2024; 14(11): 1374. CrossRef - Mature Adrenal Ganglioneuroma With Lipomatous Content: A Radiological and Histopathological Diagnostic Challenge
Mohammed Lameir Hussein, Shams O Alkhateeb, Jouhar J Kolleri, Ala' Saleem Abu-Dayeh, Khaled Murshed, Nabil Sherif Mahmood
Cureus.2024;[Epub] CrossRef - Comparative Analysis of Liquid Chromatography-Tandem Mass Spectrometry and Radioimmunoassay in Determining Plasma Aldosterone Concentration and Plasma Renin Activity for Primary Aldosteronism Screening
So Yoon Kwon, Kyeong-Jin Kim, Soo-Youn Lee, Jae Hyeon Kim
Endocrinology and Metabolism.2024; 39(6): 965. CrossRef
 PubReader
 ePub Link
 Cite
 XML Download
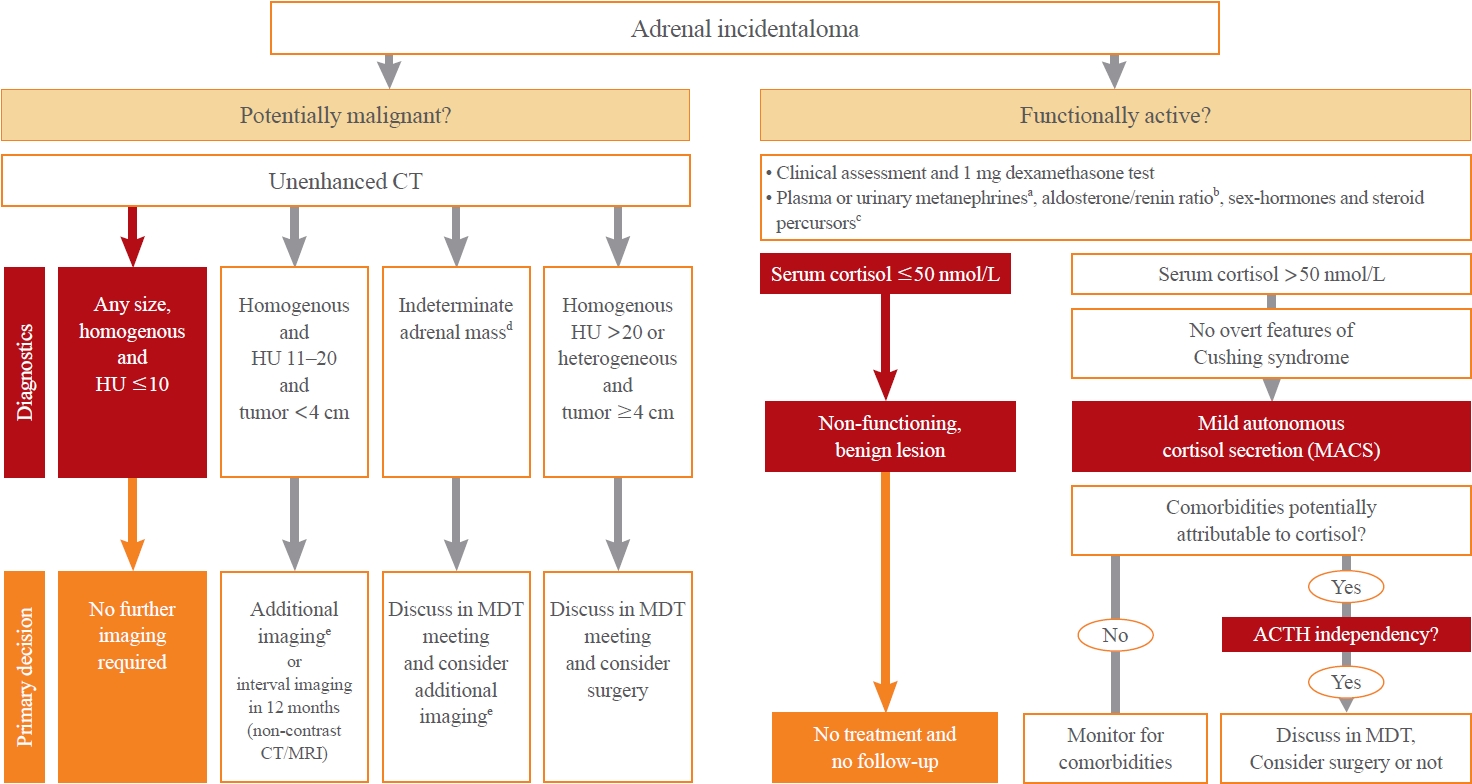
Fig. 1.
| Remarks | 2023 ESE guideline | 2016 ESE guideline | 2017 KES guideline | |
|---|---|---|---|---|
| Category for serum cortisol after 1-mg DST | Recommend: MACS |
Suggest: possible ACS |
Similar to the 2016 ESE guidelines | |
| Confirm ACTH-independency, repeat DST, consider conditions that alter the results | ACS |
|||
| Additional biochemical tests to assess the degree of cortisol secretion might be useful |
Additional biochemical tests might be required |
|||
| Treatment for patients with MACS | Recommend |
Suggest |
NA | |
| Measurement of sex hormone and steroid precursors | Suggest: ideally, use multi-steroid profiling by tandem mass spectrometry |
Suggest |
Recommend |
|
| Benign criteria for no further imaging | Recommend |
Suggest |
Homogeneous appearance, smaller than 4 cm |
|
| Management of indeterminate adrenal nodules | (1) Adrenal mass with unenhanced HU between 11 and 20 and <4 cm |
Three options |
Recommend: follow-up imaging in 3–6 months after the initial study and continuing for 1–2 years |
|
| Suggest: immediate additional imaging to avoid any follow-up imaging. | (1) Immediate additional imaging with another modality | |||
| Optional: interval imaging in 12 months by non-contrast CT (or MRI) | (2) Interval imaging in 6 to 12 months (non-contrast CT or MRI) | |||
| (2) Adrenal mass ≥4 cm and unenhanced >20 HU |
(3) Surgery without further delay. | Consider adrenalectomy |
||
| Suggest: MDT, immediate surgery/staging | ||||
| Optional: follow-up imaging in 6–12 months | ||||
| (3) Adrenal mass ≥4 cm with unenhanced HU 11–20; or <4 cm with unenhanced HU >20; or tumor size <4 cm with heterogeneous appearance | ||||
| Suggest: individualized approach in MDT | ||||
| Surgical treatment | Recommend: surgery by an expert high-volume adrenal surgeon |
NA | NA | |
| Suggest: surgical resection if indeterminate adrenal mass on imaging in children, adolescents, pregnant women and adults <40 years of age |
||||
| Hormone follow-up of nonfunctioning tumors at initial evaluation | Recommend: against |
Suggest: against |
Recommend |
|
| Follow-up of patients with MACS | Recommend: only annual re-assessment of comorbidities potentially attributable to cortisol. | Suggest: annual clinical re-assessment for comorbidities potentially related to cortisol excess. Based on the outcome of this evaluation the potential benefit of surgery should be considered. | Recommend: annual hormone tests for 4–5 years | |
| If these comorbidities develop or worsen, referral to an endocrinologist. | ||||
| Approach to bilateral adrenal incidentaloma | Suggest following four-option schema |
The same applies to the assessment of comorbidities that might be related to ACS. | Similar to the 2016 ESE guideline | |
| Bilateral (macronodular) hyperplasia or bilateral adenomas: recommend assessment of comorbidities attributable to MACS |
Bilateral hyperplasia without ACS: 17-hydroxyprogesterone | |||
| Otherwise, similar to the 2016 ESE guideline | Bilateral metastases, lymphoma, infiltrative inflammatory disease and hemorrhages: recommend assessment for adrenal insufficiency | |||
| Treatment for bilateral adrenal incidentaloma | (1) Bilateral hyperplasi |
Suggest |
NA | |
| (2) Suggest against bilateral adrenalectomy |
Suggest that bilateral adrenalectomy is not performed |
|||
Modified from Fassnacht et al. [ ESE, European Society of Endocrinology; KES, Korean Endocrine Society; DST, dexamethasone suppression test; MACS, mild autonomous cortisol secretion; ACTH, adrenocorticotropic hormone; ACS, autonomous cortisol secretion; MDT, multidisciplinary team; NA, not available; HU, Hounsfield unit; CT, computed tomography; MRI, magnetic resonance imaging. Relevant changes.


